May 15, 2020 | by Tamer Seckin, MD
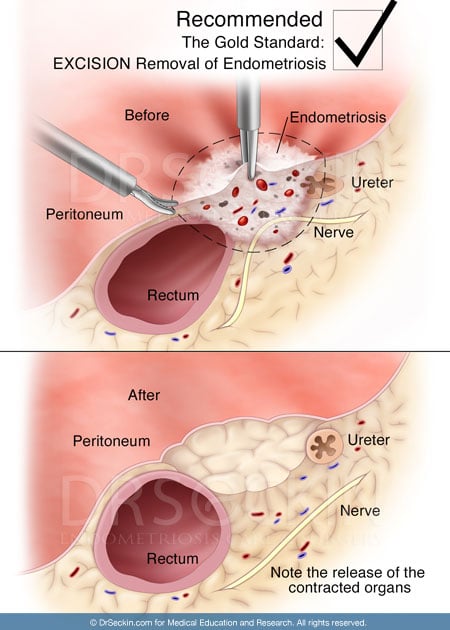
There is no cure for Endometriosis. However, several surgical and non-surgical methods exist to manage the disease, alleviate symptoms, and avoid infertility. Of these, laparoscopic deep excision surgery is the “gold standard”.
The surgeons at the Seckin Endometriosis Center (SEC) have many years of experience dealing with the most complex deep infiltrating endometriosis (DIE) lesions and have provided long-lasting relief to their patients.
Endometriosis excision surgery is often discussed as a more comprehensive approach than burning or “zapping” lesions. It aims to remove endometriosis tissue at the root, especially when the disease is deep, distorts anatomy, or involves organs such as the bowel, bladder, or ureters. That said, excision isn’t a cure, and it isn’t the right next step for every single person. The most useful way to think about it is as a powerful tool within a broader long-term plan—one that includes symptom control, recurrence prevention, pelvic rehab, and realistic expectations.
Tamer Seckin, MD, is among the distinguished specialists closely associated with Harry Reich, MD, a pioneer who performed the first laparoscopic hysterectomy in 1989.
Endometriosis excision surgery
Endometriosis excision surgery is a procedure where a surgeon carefully cuts out endometriosis tissue rather than burning it off. This technique allows doctors to remove the disease at its source, preventing it from returning quickly. Unlike ablation, which only treats the surface, excision effectively clears deep lesions that cause severe pain.
It is widely considered the gold standard treatment for long-term symptom relief and preserving fertility. Recovery typically takes two weeks, though internal healing continues for several months.
How to prepare for endometriosis excision surgery?
Preparing for endometriosis excision surgery requires organizing your home and packing the right essentials for a smooth recovery. You should pack loose clothing, slip-on shoes, and sanitary pads, as post-surgical bleeding is very common. Stock up on gas relief medication, stool softeners, and a heating pad to manage shoulder pain effectively.
Deep-clean your living space and freeze simple meals, like soups, to avoid stress during your healing week. Strictly follow your surgeon’s bowel preparation instructions to ensure the procedure goes safely without delays. Finally, arrange for a trusted friend to drive you home and assist you overnight.
Summary
Endometriosis excision surgery is a key treatment option for managing endometriosis, particularly for deep infiltrating lesions. This procedure involves the careful removal of endometriosis tissue, which can lead to long-term symptom relief and preserve fertility. While it is not a cure, it is considered the gold standard for addressing severe cases that affect organs such as the bowel and bladder.
Preparation for surgery includes organizing home care, packing essential items for recovery, and following specific bowel preparation instructions. Laparoscopic techniques allow for minimally invasive surgery with quicker recovery times, but challenges remain in accurately identifying and excising all lesions.
Endometriosis laparoscopic surgery
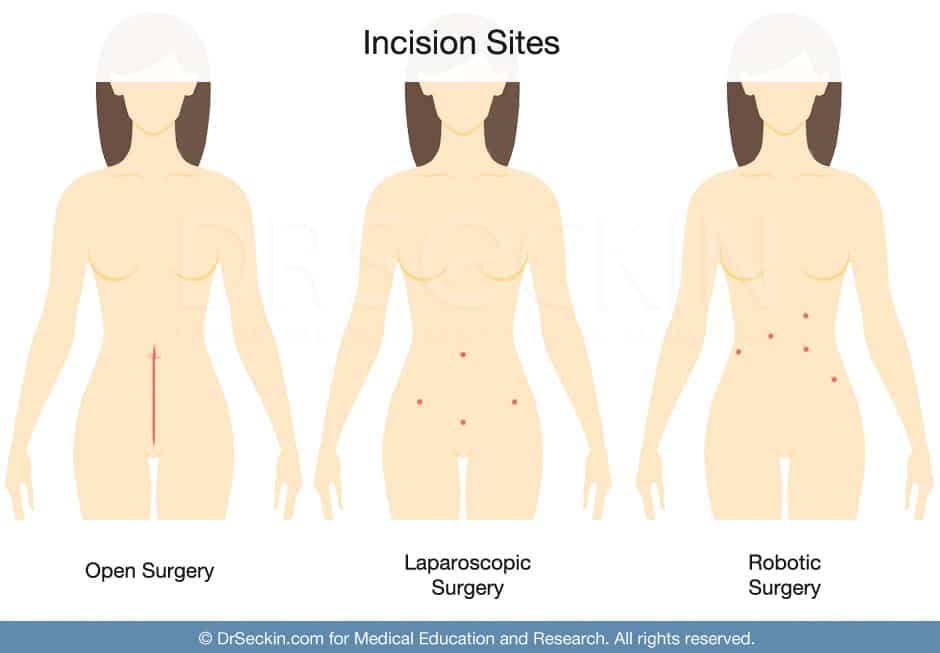
Laparoscopy, also known as keyhole excision surgery, is a type of minimally invasive surgery. Unlike open endometriosis treatment surgery, minimally invasive endometriosis laparoscopic surgery is done via small incisions that allow the entry of tiny cameras and tubes. This allows for more precision, fewer post-operative complications, reduced scarring, and shorter recovery times.
In laparoscopy, each incision is called a port. Your surgeon inserts instruments, such as a laparoscope camera, surgical tools, and a tube to pump gas into the abdomen, through these ports. The gas helps inflate the abdomen for better accessibility.
The surgeon then lets out the gas and sutures the incisions. It is possible to go back home the same day after the procedure. However, your doctor will often advise an overnight stay.
Laparoscopy can help in both the diagnosis and treatment of endometriosis.
Get a Second Opinion
Our endometriosis specialists are dedicated to providing patients with expert care. Whether you have been diagnosed or are looking to find a doctor, they are ready to help.Our office is located on 872 Fifth Avenue New York, NY 10065.
You may call us at (212) 988-1444 or have your case reviewed by clicking here.
Limitations of current techniques
Before trying to understand why laparoscopic deep excision surgery is the most effective in thoroughly removing all endometriosis lesions, we will look into some of the limitations of current approaches:
- Laser ablation removes only the top layer of the lesion and does not remove it from within. Also, laser ablation can scar surrounding healthy tissue.
- The use of heat or high energy for excision also leaves behind burnt tissue that can cause additional pain.
- Many surgeons lack adequate training to properly differentiate among the various types of endometriosis lesions. This is mainly because of the inability to properly visualize the lesions in the backdrop of the light source.
- Reconstruction and proper suturing of the incision are essential to aid repair and ensure a full recovery.
- Lack of understanding about the pan-systemic spread of endometriosis (such as thoracic or bladder endometriosis) and a dearth of multidisciplinary approaches to tackle it.
- The use of robotic-assisted laparoscopic techniques does not match the precision and tactile feedback of manual interventions.
Our approach to laparoscopic excision surgery
With years of experience, Dr. Seckin’s team at SEC has developed methods to overcome the above challenges and improve surgical outcomes while preserving the patient’s natural fertility to the greatest extent possible.
Manual excision
We follow a more hands-on approach to properly differentiate among scars, adhesions, and lesions while navigating within the body. This is simply not possible with robotic-assisted laparoscopic techniques since the surgeon has no tactile feeling of the tissue and must rely solely on video information. Also, incisions made with robotic assistance are larger than those made manually by experienced surgeons.
Dr. Harry Reich, the pioneer of laparoscopic hysterectomy, strongly favors a manual approach. This way, the surgeon can feel the disease and obtain an accurate assessment of its severity.
The lone clinical trial (LAROSE) comparing conventional and laparoscopic methods also found no meaningful difference in perioperative conditions or quality of life between the two.
Enhanced visualization strategy
We use a patented Seckin’s Aqua Blue Contrast (ABC) technique that changes the color of the peritoneum by hydro-floatation with a contrast color and retroperitoneal distention.
The advantage of the ABC technique is that it enables the surgeon to clearly visualize all available lesions even in the background of the operating light. Therefore, it becomes easy to effectively identify and isolate all visible lesions and scarring for maximum recovery.
Complete excision surgery
An endometriosis lesion is like an iceberg, with just the peak being visible while the actual bulk of the lesion is still within the underlying tissue. The underlying part of the lesion can regrow again, leading to recurrence of symptoms. Therefore, complete excision of all visible endometriosis lesions is essential for full symptom alleviation and to prevent a recurrence.
During deep excision surgery, we “core out” the lesion completely from within, so that there is no residual lesion present. This results in almost no recurrence rates in the long term and faster recovery times.
Cold excision surgery
We believe a “cold excision surgery” approach is best to preserve healthy tissue function. We do not use electricity or high energy to remove scars. This reduces the risk of tissue burns and further complications. This also helps us work with pathology teams to confirm the presence of endometrial tissue in the scar, thereby providing a definitive diagnosis of endometriosis.
Multidisciplinary approach
Endometriosis can affect not only the peritoneum and pelvic organs but also spread to other parts of the body. Treating extra-pelvic endometriosis requires involving specialists from multiple disciplines to ensure positive treatment outcomes.
At Seckin Endometriosis Center, we always follow a multidisciplinary approach that draws from the expertise of several specialties. These include pathologists, anesthesiologists, gastroenterologists, urologists, thoracic surgeons, psychologists, radiologists, and more.
Having a multidisciplinary team helps us to collectively review and provide accurate, symptom-specific advice to our patients along with positive post-operative coping strategies to ensure a smooth recovery.
Who is a good candidate for endometriosis excision surgery?
People pursue excision surgery for different reasons, and the “right” reason isn’t always based on the severity of a scan. Many patients consider excision when pain remains disruptive despite medical therapy, when there are red flags for deep disease, or when endometriosis is affecting fertility plans. Laparoscopic surgery can improve pregnancy rates in some cases compared with diagnostic laparoscopy alone, though live birth data are limited, and decisions should be individualized.
Excision is also considered when endometriosis threatens organ function, like bowel stenosis, bladder involvement, or ureteral narrowing that could affect the kidneys. In those scenarios, it becomes less about “pain management” and more about protecting anatomy and long-term health.
On the other hand, surgery is not automatically recommended for incidental, asymptomatic endometriosis discovered during another operation. Guidance cautions against routine excision/ablation in that situation because the risks may outweigh unproven benefits.
FAQs
What is the recovery time for endometriosis excision surgery?
Recovery time for endometriosis excision surgery typically ranges from 2 to 6 weeks, depending on the surgery’s extent.
Most patients can resume light activities within a few days, but full healing takes several weeks. The first week usually involves fatigue, soreness, and bloating, especially if multiple areas were treated. Walking and gentle movement help speed up recovery and prevent complications. Pain management is usually effective with prescribed or over-the-counter medications. It’s important to avoid heavy lifting and strenuous activity during healing.
Is endometriosis excision surgery painful?
Yes, endometriosis excision surgery is painful during the immediate recovery phase, but the pain is temporary and manageable with medication. Most patients report significant discomfort from the gas used to inflate the abdomen, which causes sharp pain in the shoulders and ribcage for about 24 to 48 hours. You will also feel soreness at the incision sites and deep pelvic cramping similar to a bad period.
Interestingly, many women find the surgical recovery pain less distressing than their chronic endometriosis pain because they know it is part of the healing process. Be aware that your first menstrual cycle after surgery is often heavier and more painful than usual before things improve.
Is endometriosis excision surgery worth it?
Yes, endometriosis excision surgery is widely considered the most effective long-term treatment for reducing pain and improving fertility. Unlike ablation, which only burns the surface, excision removes the disease entirely from its root. This method significantly lowers the chance of symptoms returning compared to other surgical options. Many women experience years of relief from chronic pelvic pain and severe cramping after recovery. It is especially “worth it” if you plan to conceive naturally in the future.
What is the difference between excision and ablation?
Excision surgically removes endometriosis lesions in their entirety, cutting them out from the root along with the surrounding tissue. Ablation (also called fulguration or laser vaporization) burns or destroys only the surface of visible lesions, leaving the deeper tissue behind. Because endometriosis lesions behave like icebergs — with the bulk of disease hidden beneath the surface — ablation consistently leaves residual disease that regrows. Multiple studies have shown that excision provides significantly better long-term pain relief and lower recurrence rates than ablation.
How long does endometriosis excision surgery take?
The duration depends on the extent and location of the disease. A straightforward case with minimal pelvic involvement may take 1 to 2 hours. Complex cases involving the bowel, bladder, ureters, diaphragm, or sciatic region can take 4 to 6 hours or more. At Seckin Endometriosis Center, surgeries for advanced deep-infiltrating endometriosis often require a multidisciplinary team of specialists operating simultaneously to achieve complete lesion removal in a single procedure.
Can endometriosis come back after excision surgery?
Recurrence is possible after any endometriosis surgery, but complete deep excision offers the lowest recurrence rates compared to ablation or incomplete removal. When all visible lesions are fully excised — leaving no residual disease — long-term symptom relief is significantly more durable. At Seckin Endometriosis Center, the goal is margin-free excision of every lesion in a single procedure. Hormonal suppression therapy after surgery can also reduce the risk of recurrence in some patients.
Does endometriosis excision surgery preserve fertility?
Yes, fertility preservation is a core principle of Dr. Seckin’s surgical approach. Unlike hysterectomy, laparoscopic excision removes endometriosis lesions while leaving the uterus, ovaries, and fallopian tubes intact wherever possible. Removing deep lesions — particularly those involving the ovaries or causing anatomical distortion — can actually improve natural conception rates and IVF outcomes by restoring normal anatomy. Each case is individualized based on the patient’s fertility goals and the extent of disease.
Get a Second Opinion
Our endometriosis specialists are dedicated to providing patients with expert care. Whether you have been diagnosed or are looking to find a doctor, they are ready to help.Our office is located on 872 Fifth Avenue New York, NY 10065.
You may call us at (646) 960-3080 or have your case reviewed by clicking here.